

Oncólogo colombiano. Ayudo a los pacientes con cáncer a resolver algunos de sus problemas. #PrecisionOncology #GIOncology #BreastCancer Opiniones personales.
Bogotá D.C.
Joined August 2010
- Tweets2.8K
- Following1.3K
- Followers1.3K
- Likes9.4K





Diego Felipe Ballen retweeted

#ESMO26
The drugs we’ve been enthusiastically discussing for the past three days:
Divarasib, Ivonescimab, Sonesitatug vedotin, Intismeran autogene, Tarlatamab, Zanidatamab, Izalontamab brengitecan, Gedatolisib, Giredestrant, Rilvegostomig, Torvutatug samrotecan, Savolitinib.........
OS, PFS, HR, new standards of care, changing treatment algorithms...
Then, for a moment, I returned to reality.
I can’t even offer a single one of these drugs to my patients!!!
Anyway, tomorrow we’ll be back to discussing which drug is going to change our clinical practice🤦♂️

Diego Felipe Ballen retweeted

#ESMO26 📢 PRABITAS | Phase III
📖 Simultaneous publication in The Lancet!
👥 970 pts | FTD/TPI + BEV
🔀 14-day vs 28-day schedule
✅ OS noninferior: 11.3 vs 10.3 mo (HR 0.93)
📉 G≥3 neutropenia: 13% vs 39%
💡 Same survival, less toxicity!
🔗 doi.org/10.1016/S0140-6736(2…
@OncoAlert

Diego Felipe Ballen retweeted

Adjuvant chemotherapy with cisplatin and gemcitabine compared to standard of care after curative intent resection of cholangiocarcinoma and muscle invasive gallbladder carcinoma (ACTICCA-1/AIO-HEP-0112 trial)
#ESMO26 #cancer #oncology #MedX @OncoAlert
annalsofoncology.org/article…

Diego Felipe Ballen retweeted
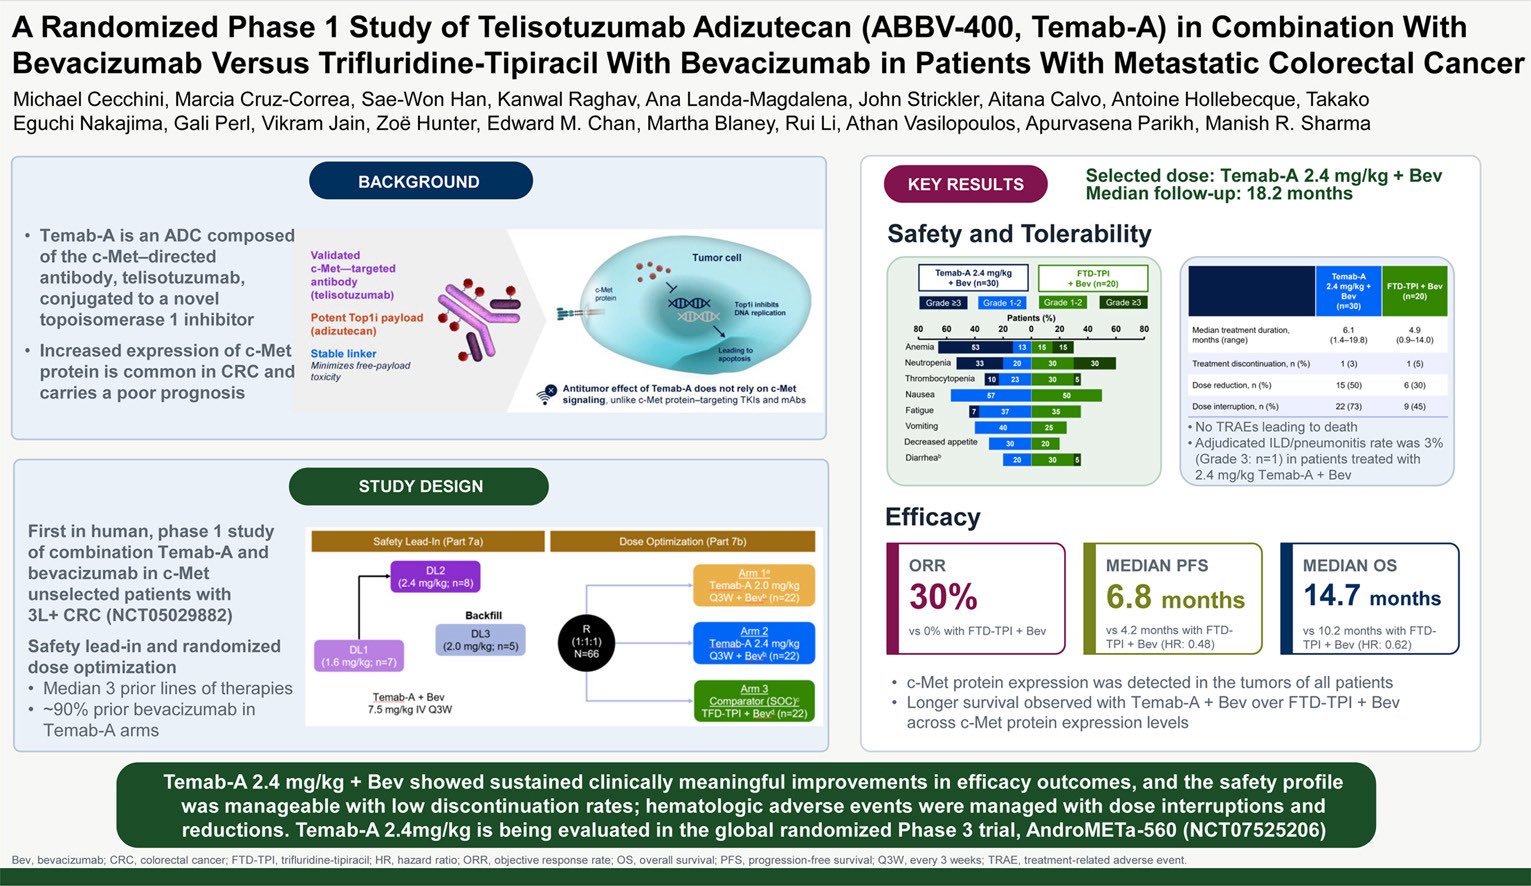
#ESMO26 🧬 ABBV-400 | Phase I
📖 Simultaneous publication in Annals of Oncology!
👥 83 pts | Refractory mCRC
💊 MET-ADC + BEV vs FTD/TPI + BEV
🎯 ORR: 30% vs 0%
📈 PFS: 6.8 vs 4.2 mo
⏳ OS: 14.7 vs 10.2 mo (HR 0.62)
🚀 Phase III ongoing!
🔗 doi.org/10.1016/j.annonc.202…
@OncoAlert
¡Es absurdo! Esto afecta a diario a pacientes con cáncer. @invimacolombia tampoco ha dado claridad: medicamentos con beneficio clínico demostrado pierden o carecen de registro sanitario por falta de interés comercial del fabricante. ¿Dónde queda nuestra soberanía sanitaria?

Les voy a contar una historia.
Martha Lucía, de 69 años, tiene cáncer de las vías biliares. Está en tratamiento oncológico y su médico ordenó continuar con quimioterapia.
Está afiliada a @Compensar_info. En septiembre, su oncólogo ordenó, entre otros medicamentos, cisplatino para continuar el tratamiento.
Pero empiezan los problemas.
Según el fallo de tutela, @Compensar_info tardó dos meses en emitir la autorización para continuar con el tratamiento. Y cuando la paciente llegó a la institución para recibir la quimioterapia, le informaron que el medicamento que necesitaba no había sido autorizado.
La familia decidió entonces comprar el medicamento con sus propios recursos para evitar que ella siguiera esperando y que se retrasara nuevamente su tratamiento.
Pero el problema no terminó ahí.
Compensar argumentó que el cisplatino estaba financiado con recursos de la UPC, pero que su uso para este diagnóstico no correspondía a una indicación aprobada por el Invima ni estaba incluido en el listado UNIRS. Por eso, según la propia respuesta de la EPS, solo podía autorizarse mediante un fallo judicial.
La paciente presentó una tutela.
Y el 8 de octubre de 2026, el Juzgado 128 Penal Municipal de Bogotá le dio la razón.
El juez concluyó que la EPS había generado una dilación indebida en el inicio y continuidad de la quimioterapia de Martha Lucía y que las barreras administrativas representaban una amenaza para su vida e integridad.
Por eso ordenó a @Compensar_info garantizar, en un plazo de 48 horas (que se cumplen mañana), el suministro efectivo del cisplatino ordenado por su médico, sin dilaciones ni trabas administrativas.
¿Imaginan la angustia de esta mujer y de su familia? Todo está documentado en una sentencia de tutela.
¿Por qué una paciente con cáncer tuvo que llegar hasta un juez para conseguir un medicamento que su propio médico había ordenado para continuar su tratamiento?
La respuesta la debería dar @Compensar_info.
¿Me ayudan a compartir, por favor, y a etiquetar muchas veces a @Compensar_info? Entre todos podemos presionar para que Martha Lucía tenga su tratamiento.

Diego Felipe Ballen retweeted

Just published! 🎉
Predictive biomarkers beyond HER2 and PD-L1 in gastroesophageal tumors 🔎
Amazing teamwork 🤩 with Dr. Alsina and @tfleitask
@myESMO @GrupoTTD @_SEOM
More info 👇🏼


Diego Felipe Ballen retweeted

CancerEfficacy and Tolerability of Zenocutuzumab in Advanced NRG1 Fusion–Positive Cholangiocarcinoma: Results From the eNRGy Phase II Trial
@JCO_ASCO
doi.org/10.1200/JCO-25-03128
👉very rare alteration, but effective treatment
@myESMO

Diego Felipe Ballen retweeted
Exercise therapy in cancer prevention and treatment
nature.com/articles/s41571-0…

Diego Felipe Ballen retweeted

New online! Right-sizing treatment for HER2-positive breast cancer: evolving algorithms across the disease continuum dlvr.it/TVqc5M

Diego Felipe Ballen retweeted
Right-sizing treatment for HER2-positive breast cancer: evolving algorithms across the disease continuum
Great review👇
@PTarantinoMD et al ✨️✨️
nature.com/articles/s41571-0…


Diego Felipe Ballen retweeted
Immune Checkpoint Inhibitor–Based Downstaging Therapy for Hepatocellular Carcinoma
#cancer #oncology #liver #hcc @OncoAlert
jamanetwork.com/journals/jam…

Diego Felipe Ballen retweeted
From operating room to pathology report: Delphi consensus on pathological assessment of peritoneal cytology and biopsies in staging laparoscopy for gastric cancer
link.springer.com/article/10…

Diego Felipe Ballen retweeted

Felicitamos a la Dra. Paula Andrea Ruiz Talero, por su nombramiento como Coordinadora Académica de la Especialización en Medicina Interna a partir del 1 de octubre de 2026, teniendo en cuenta su perfil, compromiso con la docencia, su excelente desempeño académico y liderazgo.✅

Diego Felipe Ballen retweeted

Bogotá es la única ciudad del país que adquiere vacuna contra el neumococo para personas mayores con recursos propios.
Actualmente, se está terminando la actualización de la vacuna para pasar a la conjugada en este grupo de edad. Proceso para el que ya se hicieron todos los estudios con @GES_UdeA
Las tecnologías de algo valor en Salud Pública deben ser actualizadas más rápidamente y en todo el curso vital
@Gerson_bermont

Gran avance para la salud pública: incorporar la vacuna neumocócica conjugada de 20 valencias al PAI infantil permitirá ampliar la protección frente a la enfermedad neumocócica. Ahora queda un reto importante: incluir una estrategia de vacunación contra neumococo para los adultos mayores. Necesitamos un PAI con verdadero enfoque de curso de vida. @MinSaludCol @SCPNacional

Diego Felipe Ballen retweeted
🚀Upper GI oral abstracts of #ESMO26 👇
✅Gastric/esophageal
✅Pancreatic
✅Hepatobiliary
✅NET/NEC
#cancer #oncology #MedX #GI #pancreatic #biliary #cholangiocarcinoma #liver #hepatocellular #gastric #esophageal #neuroendocrine @OncoAlert


Diego Felipe Ballen retweeted

The Health Benefits of Exercise: Molecular and Cellular Mechanisms onlinelibrary.wiley.com/doi/…

Diego Felipe Ballen retweeted
Esophageal Cancer nejm.org/doi/full/10.1056/NE…

Diego Felipe Ballen retweeted

GI Oncology saw some major changes in NCCN this week. 🔥
🧬 1. Daraxonrasib is officially in the pancreatic cancer guidelines
You knew it was coming, now it is here. Preferred, Category 1. Use it.
RASolute-302 in previously treated metastatic PDAC:
OS: 13.2 vs 6.6 months, HR 0.40
PFS: 7.3 vs 3.5 months, HR 0.45
Subsequent therapy, and importantly it also sneaks into 1L as “useful in certain circumstances,” although only 2B for fit patients (but still there, YAY).
So no, we are not throwing FOLFIRINOX/NALIRIFOX in the garbage (yet).
But a RAS inhibitor is now a standard treatment for pancreatic cancer.
🔵 2. Zanidatamab + tislelizumab in NCCN for HER2+ GEA
Zanidatamab + tislelizumab + chemo vs trastuzumab + chemo:
PFS: 12.4 vs 8.1 months, HR 0.63
OS: 26.4 vs 19.2 months, HR 0.72
NCCN now lists zanidatamab-based therapy as Preferred first-line treatment.
But… Category 2A.
Why? 2A still means uniform NCCN panel consensus (≥85%) that the treatment is appropriate (so yes, you should be using this for these patients), but officially reflects lower-level evidence than Category 1.
Except HERIZON was a randomized phase III trial with positive outcomes.
So why 2A?
Two informed guesses.
1. No US patients were enrolled. It was a large international study, and frankly the incredibly diverse patients I see in NYC probably look more like a global trial population than many historical US trials.
2. The control arm didn't include PD-1.
HERIZON compared against trastuzumab + chemo, while our current US standard for PD-L1 CPS ≥1 is pembrolizumab + trastuzumab + chemo.
But before we poo-poo HERIZON because of the comparator, let's look at what those studies actually achieved.
KEYNOTE-811, CPS ≥1:
PFS 10.9 months
OS 20.1 months
HERIZON:
PFS 12.4 months
OS 26.4 months
Of course, no one would ever compared across trials. 😅
But HERIZON's own trastuzumab/chemo control arm had an OS of 19.2 months. This wasn't a control arm falling over.
To me, these data show a real advance in HER2 therapy.
If you’re using it, do watch for the diarrhea.
NCCN specifically recommends antidiarrheal prophylaxis with zanidatamab and avoiding bolus 5-FU. Grade ≥3 diarrhea was 24.8% with the quadruplet but can be controlled and is only during the first few treatments.
3. And very briefly, MATTERHORN
FLOT + durvalumab was upgraded 2B → 2A for PD-L1 <1 and diffuse-type EGJ adenocarcinoma.
Overall MATTERHORN: 2-year EFS 67.4% vs 58.5%, HR 0.71, with pCR 19.2% vs 7.2%.
Love seeing forward progress in GI Oncology.
@TheGutOncLab @OncoAlert @Onco_Nexus @oncodaily
Diego Felipe Ballen retweeted
8th International Consensus Guidelines for the management of advanced breast cancer (ABC8 Guidelines)
thebreastonline.com/article/…

Diego Felipe Ballen retweeted
MATTERHORN final results: a 7% absolute improvement in 3-year OS with perioperative durvalumab + FLOT (69% vs 62%; HR 0.78).
Periop durvalumab + FLOT: SoC ✅️
However, I still have concerns about the magnitude of benefit in diffuse-type and PD-L1–negative disease.
thelancet.com/journals/lance…

