

South Holland, The Netherlands
Joined May 2018
- Tweets86
- Following0
- Followers138
- Likes46







Congrats Ken Masdjedi with your PhD -advancements coronary physiology #ffr #iFR #vFFR #dPR @CathlabN @ErasmusMC @drnvanmieghem @jescand @BernardBruyne @nielsroyen

Announcing #IVUS #CHIP trial for #highrisk #complexpci patients with #IVUSguidance
@PCRonline @TCTMD @ErasmusMC @hect2701 @mirvatalasnag @KambisMashayek1 @JEscaned @sbrugaletta @RinfretStephane @esbrilakis @CathlabN
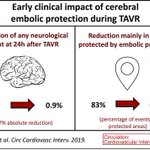
H.Kroon et al compared largest #TAVR #TAVI group to date with/without #CerebralEmbolicProtection bit.ly/2FdKaNy @PCRonline @TCTMD @hect2701 @mmamas1973 @dmylotte @nicolo_piazza @didier_tchetche @pauldub67 @DrPascalMeier @escardio @DFCapodanno #cardiotwitter

R.Diletti presenting @ErasmusMC / @CathlabN #FFR Search 2 yr data #europcr @pcronline #cardiotwitter @TCTMD @escardio – at Paris, France

Good luck Paula Scarparo with #FFR after #PCI #EuroPCR ‘s got talent @CathlabN @hect2701 @pauldub67 @DFCapodanno @SABOURETCardio @sbrugaletta @erasmusmc @mmamas1973 #CardioTwitter

Congrats Eric Boersma @ErasmusMC , you are now officially #WorldClass , thank you for mentoring / teaching #ThoraxCenterEMC teams to the top !
#cardiotwitter #cardioed @mmamas1973 @DrPascalMeier @sbrugaletta @pauldub67 @escardio @PCRonline @TCTMD @ajpeace74 @rbcasado @hect2701

9/ #Tweetorial Return retrogr w fast advancement knuckle wire @lorenzo2509 @cghanratty @jcspratt @KambisMashayek1 @sbrugaletta
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
8/ #Tweetorial -Strategy after tip-in technique
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline @sbrugaletta @hect2701
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO


7/ #Tweetorial neo-ostium created >tip-in techn w anteg micro-cath
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline @sbrugaletta
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO

6/ #Tweetorial - Knuckle wire > no micro-catheter advancement
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline @sbrugaletta
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
5/ #Tweetorial - R.Diletti - Retrograde wire escalation (Gaia 2) @lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
4/ #Tweetorial - Shift to #retrograde to correct #antegrade complication
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO

3/ #Tweetorial #CTO - difficult #wire pullback, #microcatheter stuck in calcium
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
We tried to follow the wire with the MC but it became stuck in the calcium. We retracted the wire and attempted the #Carlino technique and discovered that contrast was in the pericardium (we didn't save this run, sorry guys).
2/ #Tweetorial - R.Diletti - initial #retrograde fail ,switch to #antegrade @lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
1/ #Tweetorial - R.Diletti - Management #CTO #ostial #perforation with J-CTO 3)
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
Initial angio with ostial RCA CTO, epicardial collateral up to mid segment RCA. 2nd occlusion in mid distal segment. Small septal collaterals perfuse the distal RCA. @RinfretStephane #cardiotwitter
#tweetorial, how would you manage an #ostial #CTO #perforation w micro-catheter tip in pericardium ?
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO
12%MC out>pericardiocentesis
42%Neo-ostium(our case)
38%Covered stent ostial CTO
8%Other (please discuss )
26 votes • Final results#tweetorial Initial situation #ostial perforation w micro-catheter in pericardium. Final tweet is Poll
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @pauldub67 @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO

10/10 Externalisation/Finalisation "We hope u enjoyed #Tweetorial" (r.dilletti/@pauldub67 )
@lorenzo2509 @cghanratty @jcspratt @KambisMashayek1
@esbrilakis @GreggWStone @RinfretStephane @mmamas1973 @PCRonline
#CTO2019 @EuroCtoClub @MLCTOcourse @OptimalCTO

