

Urologist, Robotics, Uro-Oncology, Recon
Edinburgh, Scotland
Joined January 2016
- Tweets2K
- Following137
- Followers47
- Likes4.2K


Daniel Good retweeted

This meta-analysis confirms what the technique promised: early apical release halves the risk of early SUI after HoLEP (RR 0.47 at 4–6 weeks, 0.44 at 3–4 months) across 2821 patients.
pubmed.ncbi.nlm.nih.gov/4289…

Daniel Good retweeted

Among the big news from #ESMO2026: PROTEUS companion RCT (not a substudy ¯\_(ツ)_/¯ ) comparing neoadj apa/ADT to RP alone. Impressive early results, should put to rest at least some of the objections to PROTEUS main paper.


Daniel Good retweeted

@drjkaouk showing his impressive urinary and sexual outcomes at 12 months with TV radical prostatectomy (n=346) @CleClinicUro SP Symposium
@elbyaty @KarimDaherMD @SalimKYounis1 @ricautor @vourganti @MWatfa26


Daniel Good retweeted

📣 EDITORIAL: Metastasis-free Survival in High-risk Prostate Cancer: A Valid Surrogate, but Is it Transportable Across Strategies of Unequal Systemic Exposure? by Michael Baboudjian et al
Read the full article: buff.ly/ubFCVxw
✨ We thank the authors for the valuable contribution to EUO!
@uroweb
@mroupret
@GPloussard
@jteoh_hk
@Ric_Campi
@CaPsurvivorship
@LauraMarandino
@DaveDandrea
@RenuEapen
@Ecastromarcos
@OncoAlert
@Sciencedirect

Daniel Good retweeted

A commonly found gut microbe manufactures a molecule that is capable of slashing cholesterol levels and shrinking plaque in arteries
go.nature.com/4y50J5X

Daniel Good retweeted

Thank you for your YouTube presentation @NicholasZaorsky .
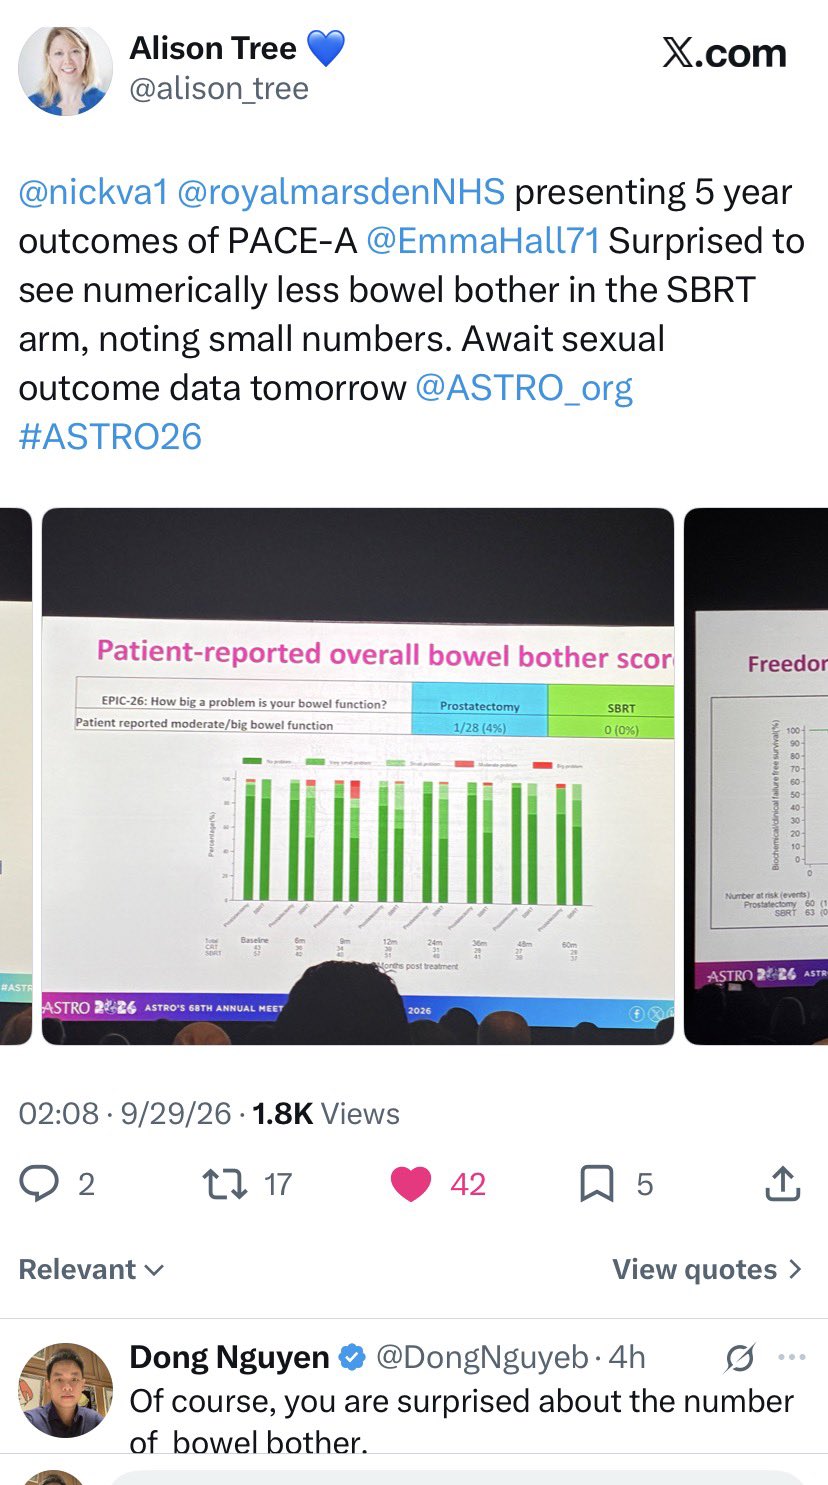
However, your talk provides incomplete information about the PACE-A study, both regarding efficacy and toxicity of SBRT vs RP.
To help readers get more clarify information.
PACE-A was originally designed as a non-inferiority trial to demonstrate oncological efficacy, the BCF, of SBRT vs RP.
But, in fact, PACE-A changed its primary endpoint from BCF to patient report functional outcome and not follow the non-inferiority design anymore.
So, the new primary endpoint is a co-primary PRO: number of pads >= 1 per day (one of these questions about urinary function in EPIC-26) and bowel EPIC score.
The reason stated in the protocol was that accrual was too slow, making it no longer feasible to demonstrate non-inferiority in disease control.
However, even after changing the primary outcome and reducing the sample size for the PRO, the new sample size target was still not met. (Enroll: 123 , target: 234)
The oncology efficacy, BCF endpoint is now a secondary outcome; although median follow-up was 8 years, it must be emphasized that the sample size is rather small and the number of events is low (13 events).
Therefore, the fact that BCF did not reach statistical significance in this study cannot be used to conclude that SBRT and RP are "basically, it's the same," as you claimed in your video.
@nickva1 , @alison_tree

Daniel Good retweeted

@"PART (Partial Ablation vs whole gland Radical Treatment) trial protocol published in BJUI"linkedin.com/pulse/part-part… on @LinkedIn

Daniel Good retweeted
If you want to use your PACE-A study to counsel patients, then you must state clearly and honestly that this is a study with a small sample size that failed to meet its accrual target, even after you were changing the primary endpoint at mid-study from an oncological assessment (biochemical recurrence) to a patient-reported functional outcome, which is prone to bias from self-reporting.
In addition to failing to meet the sample size target, the questionnaire response rate was low and the amount of missing information reached ~ 50% in each arm.
Therefore, any estimates drawn from it are entirely uncertain.
Furthermore, we object to your use of the conference #ASTRO to disseminate misleading information: replacing the co- primary endpoint of bowel function assessment by EPIC-26 bowel domain score which was unfavorable to SBRT to patient-reported moderate/big bowel function, thereby making the results appear nearly balanced between RP vs SBRT.



Daniel Good retweeted

I caution early celebration – perhaps wait for the 20 year ProtecT publication. The 15-year report had a sneak peek at PCa specific death between 15 and 20 years. For radiation was 7 times higher than prostatectomy and 3.5 times higher than active monitoring.

Daniel Good retweeted

🚨 In advanced #ProstateCancer, BRCA status correlates with response to AR-directed therapy 🚨
@CRC_AACR @AACR, pooled analysis of 5 randomized ARPI trials (apalutamide or abiraterone):
👥 608 pts on ARPI-based regimens, HRR status by tissue or plasma sequencing
📊 Retrospective pooled biomarker analysis, endpoints rPFS and OS
✅ BRCA-altered pts did worse on ARPIs:
Progression HR 1.8 (1.16-2.79) p=0.009,
Mortality HR 1.6 (1.02-2.34) p=0.038
✅ HRR-altered (any) had shorter
rPFS, HR 1.7 (1.2-2.3), p=0.001
✅ HRR-altered men still benefit from intensifying: adding ARPI to ADT prolonged:
rPFS HR 0.42 (0.2-0.89)
OS HR 0.45 (0.23-0.91)
⚠️ Retrospective, ARPIs limited to Apa/Abi. Hypothesis-generating for combinations
🎯 HRR and especially BRCA alterations = aggressive biology, still, they benefit from ARPi benefits
🔗 doi.org/10.1158/2767-9764.CR…
@UroOnc @PCFnews @PCF_Science @SUO_YUO @UrologyTimes @urotoday


Daniel Good retweeted

I’m not sure this framing advances the discussion.
Calls for level 1 evidence for focal therapy were reasonable and based in fact. Claims that radiation is the “new gold standard” over surgery deserve the same scrutiny. ProtecT did not establish radiation’s superiority over surgery and to the contrary actually confirmed equivalence. Our evidentiary standards should be consistent across treatments.
Surgery and radiation are both excellent options, with different side effect profiles. Patient preferences often guide the choice after informed decision making with both rad oncs and Urologists.
We owe our patients balanced, evidence-based counseling. Overstating the evidence risks eroding trust with both patients and colleagues.

Controversial statement by @SJFrankMD, informed by the ProtecT study results, for those who still think prostatectomy is the better treatment. #ASTRO26

Daniel Good retweeted

Endoscopic outlet surgery for BPH reduces the incidence of new-onset depression and anxiety by 30% compared to medical management. Consider surgical intervention for patients at risk of these mental health issues. tinyurl.com/2xqpmru9 @SocietyofBPD
Daniel Good retweeted

🚽 Is Gem/Doce the Future for Bladder Cancer Treatment?
Gem/Doce shows promise as a first-line treatment for BCG-naïve high-risk NMIBC, offering new hope during BCG shortages.
📈 Efficacy - 3-year high-grade recurrence-free survival is 80%
🔬 Tolerability - Only 8% stopped due to adverse reactions
📊 Future Potential - Phase 3 trials needed for standard care status
#BladderCancer #GemDoce #ClinicalTrials
tnyp.me/xRumFw21/x

Daniel Good retweeted

@ARRODRIGUEZMD debating why salvage RP is best option for radio-recurrent disease.
@wakeurology @FocalSociety @SocietySURS @Endo_Society


Daniel Good retweeted

PROTEUS moves radical prostatectomy into a multimodal era: perioperative apalutamide plus ADT reduced the risk of metastasis or death by 20%. The next challenge is selecting who truly needs intensification.
🔗[doi.org/10.1038/s41391-026-0…] #ProstateCancer
🤖 Made with AI

Daniel Good retweeted
Delighted to share our newly published PART trial protocol paper bjui-journals.onlinelibrary.… #focaltherapy #prostatecancer @NDSurgicalSci @SITU_Oxford @NIHRresearch @QuinteTBristol @PART_Trial @BJUIjournal We continue at pace to deliver high level evidence in the field

Daniel Good retweeted

Here's a visual summary:


Incredible, fascinating genetic studies and epidemiology for hereditary lung cancer in non-smokers, led by @DanaFarber researchers
Germline EGFR T790M mutation and lung cancer risk | Science science.org/doi/10.1126/scie…

Daniel Good retweeted

I would decompress the bladder with a Foley/SPC. Then treat it like a complex IVC filter removal. Get a big sheath in the IJ. Grab the stent with rigid forceps and pull out stent. Get a cystogram in a few weeks to check on bladder healing, pull the Foley/SPC when healed. #irad

Transfer center call: Patient presented with E. coli bacteremia and was found to have a ureteral stent extending from her bladder through the IVC directly into her Right Atrium. What would you do?

ALT CT images showing double J stent passing from the bladder through the inferior vena cava into the right atrium of the heart. (A) Coronal view. (B) Sagittal view.
Daniel Good retweeted
Urinary diversion for severe pelvic radiation injury significantly enhances bowel-related quality of life. Urologists should consider this intervention for patients with debilitating post-radiation complications. tinyurl.com/26to34nz

Daniel Good retweeted

Amazing live partial nephrectomy of hourglass-shapes tumor extending from cortex to renal sinus by @NNHarke
New trick: needle brought through port to puncture the renal pelvis and filling it with air to check for bubbles after calyx suture @ERUSrobotics
