
IBD Specialty Clinical pharmacist @UofTPharmacy @UF alumna #IBDPharmD IBDPatient Tweets are mine =Opinions 🚫medical advice 🇨🇦🇺🇸
California, USA
Joined April 2012
- Tweets2.4K
- Following238
- Followers620
- Likes5.8K






Pinned Tweet
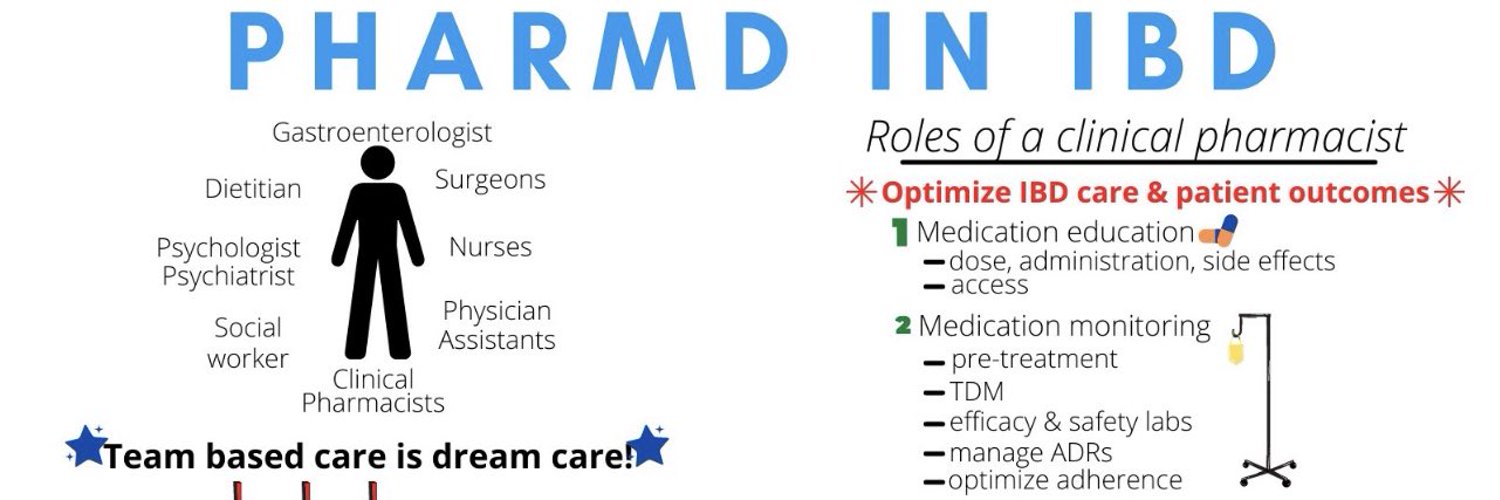
Roles of Clinical #PharmD in management of #IBD
@MondayNightIBD
#TwitteRx #GITwitter
#ClinicalPharmacist #IBD

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

Sometimes, we re-induce.
Is IV or SQ re-induction better for Risa?
✅(👇) @AGA_CGH @AmerGastroAssn
▶️NR to IV induction in #UC at wk 12
▶️Randomized to SQ vs IV re-induction
▶️SQ = IV (Fig 2a)
Re-induction vs stay vs switch? a more interesting Q!
cghjournal.org/article/S1542…

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

#MondayNightIBD 🎥series kicks off w/ @EdLoftus2 & @DCharabaty discussing #IBD RCTs (&🆓 #CME) teapawt.org/i/broadcasts/2JQeRAqpJ…

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

Management of C diff infection in patients with IBD - AGA Clinical Practice Update 2026

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

🛑Before reducing upadacitinib to 30mg in UC, check for clinical and biochemical remission. These--not how long on 45mg--predict adverse outcomes
➡️Our practice: check PROs and FC at 6 weeks to guide dosing past 8wk
🥳to @sarah_rotondoMD and @rajdalalmed on this impactful work!

When is it safe to de-escalate upadacitinib from 45 mg in UC?
In our newly published study, clinical and biochemical remission—not duration of induction—predicted successful dose de-escalation.
Treat the patient, not the calendar. 🎯
Read more: doi.org/10.1093/crocol/otag1…

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

Trials for combination therapy in IBD: @SaraLewinMD @ucsfibd


Personalized treatment selection in Crohn’s disease: integrating prior biologic exposure, EIMs, and disease phenotype to guide the next therapy.
#IBD #CrohnsDisease #PrecisionMedicine @ucsfibd

🧬 Obesity can alter biologic pharmacokinetics in IBD, increasing drug clearance and potentially reducing drug exposure. An important consideration for optimizing therapy.
#IBD #Pharmacokinetics @ucsfibd

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
The @ucsfibd group gets ready for the speed round highlighting all the innovations in care @UCSFHospitals @RishikaChughMD @SaraLewinMD @KendallBeckMD @JustinFieldMD @RMosadeghi @RishikaChughMD @priyakathpalia #SarahGuelfi

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
Our @iUSCAN @BowelUltrasound star @RishikaChughMD talking about the role of IUS in pregnancy @ucsfibd conference and importance of monitoring and predictive value of active disease on IUS


B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
Peptides for IBD… no data at this time


Risk of hormone therapy and IBD presented by @JustinFieldMD. Older age increased risk of VTE with IBD and improvement in IBD symptoms with HRT for menopause. @ucsfibd


B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
Older IBD pts (>60) will make up 1/3 IBD pts by 2030! That’s why @KendallBeckMD @ucsfibd @UCSFHospitals founded the first longevity clinic in the US in collaboration with @UCSFGeriatrics. unique challenges- frailty, sarcopenia, polypharmacy and under treatment of IBD


So great to see a clinical GI IBD pharmacist giving a talk at the conference @ucsfibd . It’s always so important to include Pharmacists as a core member of the multidisciplinary team. Their expertise truly elevates patient care. 💊👩⚕️
#IBD #ClinicalPharmacy #MultidisciplinaryCare
Our amazing GI clinical pharmacist Sarah Guelfi teaching us how and when to order GLP1 in IBD. @ucsfibd


B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
Risk of hormone therapy and IBD presented by @JustinFieldMD. Older age increased risk of VTE with IBD and improvement in IBD symptoms with HRT for menopause. @ucsfibd
B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
Great couple of slides lining up the IL23 agents in UC. @ucsfibd @bruce_sands1


The 21st annual @ucsfibd conference kicks off with @bruce_sands1 and a state of the art lecture on UC. So how can appendectomy be both a risk factor for extension of proctitis AND a possible treatment? Interesting.


B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
The 21st annual @ucsfibd conference kicks off with @bruce_sands1 and a state of the art lecture on UC. So how can appendectomy be both a risk factor for extension of proctitis AND a possible treatment? Interesting.
B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

🧪 Perianal fistulas clear infliximab faster
📍 ATLANTIC: prospective PK cohort, 148 patients on standard IV infliximab 5 mg/kg (62 perianal fistulizing CD vs 86 luminal CD)
📈 +23% clearance in progressive perianal disease (TOpClass ≥2c) during induction
🎯 Week 14: only 9% of PFCD patients reached their target trough (≥10 µg/mL) vs 46% of luminal CD (≥5 µg/mL)
🩸 Median trough at week 14: 2.9 vs 4.8 µg/mL
💡 Authors' case: front-loaded induction plus early TDM in PFCD
⚠️ Single centre, PK study, different targets per phenotype. No RCT yet of intensified vs standard induction
👇 Key numbers in one image
🔗 doi.org/10.1093/ecco-jcc/jja…
#MedTwitter #GITwitter #MedEd #IBD #CrohnsDisease #PerianalCrohns

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

Two routes to breaking the therapeutic ceiling in IBD, on one timeline.
New drugs, if the trials succeed: the first anti-TL1As and obefazimod could reach Europe in 2028, and the first oral IL-23R peptide in 2029.
Combinations: all three phase 3 readouts land in 2027 and 2028. The first two-in-one injection could follow around 2031.
Next on Atomic IBD: the tablets, and whether they’ll arrive as partners rather than on their own.

B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted
DUET tests JNJ-4804, J&J’s guselkumab plus golimumab co-formulated in one subcut injection, in two phase 2b trials, one in UC and one in Crohn’s disease.
These were big studies: 572 patients with UC; 693 with CD; every patient having previously failed at least one advanced therapy.
The main results were at DDW in May, with more on the most refractory patients at UEG last week.
At week 48, high-dose JNJ-4804 beat golimumab in both diseases. Against guselkumab, clinical remission was 41% v 34% in UC and 51% v 43% in CD, differences that were not statistically significant.
The bigger differences came in patients who had already failed two or more therapy classes, about half of each trial population.
CD: 49% clinical remission on the high dose combo vs 27% on guselkumab mono.
UC: 27% (12 of 45) on combo vs 16% (8 of 50) on guselkumab mono and 2% (1 of 47) on golimumab mono. These are exploratory subgroup analyses with wide confidence intervals.
On safety, serious adverse events to week 48 were highest on placebo and golimumab, the arms with the least disease control. That fits the placebo-harms meta-analyses published in @LancetGastroHep in 2024.
The phase 3 trials, DUET ENCORE, compare JNJ-4804 with guselkumab mono in 644 people with UC and 460 with CD, with primary completion expected in 2028.
As with many big, complex and important trials, the full papers will give critical details not yet in the public domain, and help show where this approach fits.


B. Evana Ghassemi, PHARMD, BCACP, BCPS retweeted

🔥 HOT FROM ACG 2026 | NASHVILLE
Five IBD Studies Worth a Closer Look!
Another exciting ACG meeting, another opportunity to reflect on where IBD care is heading.
From innovative drug delivery strategies to better symptom control, complex patient populations, and reproductive health, the science continues to evolve.
For this special edition of IBD Library™, we invited Dr. @AsadurRahman87 , Medical Director of the IBD Center and Associate Program Director of the GI Fellowship at Cleveland Clinic Florida, to review five interesting studies presented at ACG 2026.
🔬 What's inside?
💉 Subcutaneous vs IV infliximab: Could route of administration influence outcomes in ileal Crohn's disease?
💊 Risankizumab AFFIRM trial: Another step toward an entirely subcutaneous treatment strategy.
🌙 Obefazimod in UC: Because bowel urgency and uninterrupted sleep matter to our patients.
🩺 JAK inhibitors in PSC associated IBD: Exploring options for a particularly challenging population.
👶 Fertility and IBD: Encouraging insights from the WIsDoM cohort on assisted reproductive technology.
Innovation in IBD is no longer just about introducing another effective molecule. It is also about how we deliver treatment, what outcomes we prioritize, and how we address the needs of patients often underrepresented in clinical trials.
Of course, conference abstracts generate important questions, but not necessarily immediate changes in practice.
A special thank you to Dr. Asad ur Rahman for contributing his expertise to this edition of IBD Library™.
📖 Enjoy the review, and let us know:
Which of these five studies caught your attention the most?
#IBDLibrary #ACG2026 #CrohnsDisease #UlcerativeColitis #IBD #Gastroenterology #ClinicalResearch #MedicalEducation
🤖 Made with AI
