

Cardio/CC friendly nephrologist. In love with POCUS, cardiorenal & critical care medicine. Tweets reflect my own personal opinion
Kansas, USA
Joined February 2012
- Tweets3.2K
- Following500
- Followers1.8K
- Likes6K





Ahmed T Abdellah retweeted

What is VExUS actually measuring?
A new multicentre study provides a useful answer.
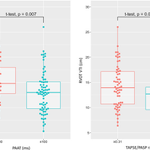
D’Alto and colleagues studied 187 patients referred for pulmonary hypertension assessment across 7 centres. VExUS was performed within one hour of right-heart catheterisation, allowing direct comparison with invasively measured right atrial pressure (RAP).
The relationship was striking:
VExUS 0: mean RAP 3.9 mmHg
VExUS 1: 8.4 mmHg
VExUS 2: 13.5 mmHg
VExUS 3: 15.8 mmHg
For identifying RAP >12 mmHg, VExUS had an AUC of 0.97.
The association held across patients with precapillary pulmonary hypertension, postcapillary pulmonary hypertension and those without pulmonary hypertension.
What does this tell us?
VExUS is often discussed as a tool for assessing “volume status” or “venous congestion”.
But these data reinforce a more precise interpretation:
VExUS is primarily a marker of the venous pressure environment, especially right atrial pressure and its transmission into the systemic veins.
High RAP is not the same thing as excess intravascular volume.
RAP may be elevated because of:
• RV dysfunction or RV–pulmonary arterial uncoupling
• severe tricuspid regurgitation
• pericardial constraint
• raised intrathoracic pressure
• pulmonary hypertension
• excess circulating volume
• or a combination of these
So an abnormal VExUS score tells us that systemic venous pressures are high.
It does not, by itself, tell us why they are high and it does not automatically mean the patient needs diuresis or fluid removal.
The key takeaway:
VExUS appears to be an excellent non-invasive marker of elevated RAP.
Use it to identify an adverse venous pressure state.
Then work out the mechanism
@ThinkingCC @NephroP
journal.chestnet.org/article…

Ahmed T Abdellah retweeted
Blood Doesn't Flow Because of Pressure
On misreading equations as mechanisms
We are taught that blood flows because of a pressure gradient.
It is one of those statements that is true enough to be useful and simple enough to be dangerous. It gives us a clean mental model: the heart generates pressure, pressure is higher in the arteries than the veins, and blood flows down the gradient.
The equation seems to confirm it:
Q = ΔP / R
Flow equals pressure difference divided by resistance. Pressure difference sits on the right-hand side. Flow is the output. The story almost writes itself.
But the equation does not say what we often make it say.
It describes a relationship between variables in a solved system state. It tells us that, for a given flow through a given resistance, there must be a corresponding pressure difference. It does not tell us that the pressure difference is the independent cause of the flow.
That causal interpretation has to come from somewhere else. It has to come from the physics.
And the physics is more interesting than the shorthand...
Read on for free on my Substack. substack.com/@icmteaching/no…

Ahmed T Abdellah retweeted

High-output heart failure associated with arteriovenous fistula remains an underrecognized, albeit well-described, clinical entity. This is a nice case with illustrative images - doi: 10.1016/j.jaccas.2026.107193. PMID: 41770183
#POCUS #Nephpearls

Ahmed T Abdellah retweeted
A lot of haemodynamic confusion comes from one basic error: treating descriptions of the system as if they were causes.
Pressure gradients, preload, RAP, afterload, Starling... all are useful, but often misread.
This review tries to put them back together into a coherent framework.
doi.org/10.1111/anae.70238


Ahmed T Abdellah retweeted

An intriguing spectral Doppler pattern. A patient with normal biventricular size and function. CW Doppler interrogation across the tricuspid valve in 4 chamber view is shown, consistently yields systolic diastolic flow. Whats are possible explanation?

Ahmed T Abdellah retweeted

PAD reduzida no choque hemodinâmico é sempre sinônimo de vasoplegia? Nem sempre!
Entenda situações em que a PAD perde acurácia nessa associação.
Segue o fio 🧶

Ahmed T Abdellah retweeted

#mdpijcm #ResearchPaper Sharing
Title: The VTI-VeXUS Index in Septic Shock: An Exploratory Proof-of-Concept Observational Study of a Novel Hemodynamic Parameter
Citations: 4
📌link: mdpi.com/2077-0383/14/16/577…
✍by Dr. Ross Prager et al @ThinkingCC
@JCM_MDPI

Ahmed T Abdellah retweeted

Our paper is out! VExUS + LUS reflect intracardiac pressure changes before and after decongestion in critically ill patients: journals.lww.com/ccejournal/…
@ArgaizR @ElliottMillerMD @sacalle1 @NarulaSukrit @YaleIMed @TradIMYale

Ahmed T Abdellah retweeted

A common Q in acute HF is what dose of diuretic to start with. In this pilot RCT we tested a simpler strategy of just giving 1 gram of lasix over 24 hrs to everyone even if diuretic naive. We saw more urine, lower venous pressure and no drop in CO or gfr
doi.org/10.1093/ejhf/xuag069

Ahmed T Abdellah retweeted
One of the important echo studies highlighting the importance of EARLY systolic notching of RVOT PW Doppler signal in patients with pulmonary embolism. This finding is present in >90% of patients with significant pulmonary embolism but it is uncommon in low risk/low thrombus burden patients. It is more prevalent than other well known echo phenomena, such as McConnell's sign, 60/60 sign, etc
onlinejase.com/article/S0894…

Ahmed T Abdellah retweeted
Scary #echofirst image
Clot in transit - though both TV and MV😱
#POCUS #FOAMed #FOAMcc
See thread for 🔗 to source/full case.
Ahmed T Abdellah retweeted
Interesting #echofirst image
SLE -> stroke 🫀👇
#POCUS #FOAMed
Source 🔗CASE (Phila). 2020;4(6):507-511. doi: 10.1016/j.case.2020.09.005.
Ahmed T Abdellah retweeted
CW Doppler interrogation across the aortic valve in 5-chamber view. What does this tracing demonstrate?

Ahmed T Abdellah retweeted
🧵 Thread: Why cardiovascular physiology feels confusing (even to experts)
Part 1 of my 'The physics of circulation' series
Cardiovascular physiology isn’t confusing because it’s complex.
It’s confusing because we routinely mix up description with causation. And our language subtly reinforces the error.
🤖 Made with AI
Ahmed T Abdellah retweeted

Ahmed T Abdellah retweeted

Patient with fevers, dyspnea, and hemoptysis. You place the echo probe and see this 😰
What's the diagnosis?
Here are some tips as an echo-loving ICU doc👇
Ahmed T Abdellah retweeted

An 88-years-old woman with dyspnea.
#echofirst