

Spine neurosurgeon with a focus on revision and complex minimally invasive surgery. Posts reflect interesting cases and skepticism
Columbus, Ohio
Joined March 2017
- Tweets204
- Following69
- Followers928
- Likes334




Another phenomenal match. We are pumped to have you join the family!


2
10
474
If you see a patient with pseudoarthrosis and proximal junctional failure after an L2-S1 fusion, what is the worst possible treatment plan? See below:
This patient had L1-2 PJF on top of an L2-S1 fusion (pseudoarthrosed). For unknown reasons, he underwent hardware removal, and then an open L1-2 laminectomy. Needless to say, 6 months later he's in bad shape and now can't walk or stand.
What would you do?
#Neurosurgery #spinesurgery


Congrats to our graduating chiefs!! I am proud and blessed to have been able to be a part of your training. You've all learnt a ton, but have also taught me much. All of the faculty look forward to your successes!! @asadsakhter @DanKreatsoulas @JoravarDhaliwal @NeurosurgeryOSU

Not to steal @drmikeselby 's thunder, but seriously, how is ALIF not the best approach for L5-S1 spondy's?
Recent case involving a Grade 2 with a high PI (88). During the ALIF, putting a roll under the buttock and using angled instruments made the disc space readily accessible.
Equally important as the interbody are the screws. Interbody distraction only gets you 50% of the way there in terms of reduction! If you do perc screws, you have to use a system that has powerful reduction capabilities. Globus (NuVasive) Reline has been my workhorse for years - the movie shows why.


I did as many commented and used preop traction to get a little bit of distraction (30%). What helped the most was then following it up with in-situ plate distraction - distracting against a rod holder and the occipital plate. Needed strong distal fixation while minimizing length so I put in pedicle screws at C2-3 with nav. Video below showing the plate distraction and the post-op results. Also removed the integrated C1 lamina.
Patient did very well and recovered hand strength at 3 months, still working on balance training.
#neurosurgery #orthotwitter


This is a young patient in her 30s who presented with worsening myelopathy. Hands are weak, balance is off - can't walk/jog without falling. Imaging shows this...
What's going on and what would you do? Before anyone talks about cervical interbodies, look at the angulation of the OC (or is it C1-2?) joints... and the sole left vertebral artery course.
#Neurosurgery #orthotwitter

This is a young patient in her 30s who presented with worsening myelopathy. Hands are weak, balance is off - can't walk/jog without falling. Imaging shows this...
What's going on and what would you do? Before anyone talks about cervical interbodies, look at the angulation of the OC (or is it C1-2?) joints... and the sole left vertebral artery course.
#Neurosurgery #orthotwitter
Congratulations to our newest colleagues!!
Excited to announce our incoming intern class at The Ohio State Neurosurgery Program!! Welcome @bhenderu @jmamarildavis @MynorMendez_ and Nicco Ruggiero!!

ALT Pictures of our inter class
15
1,073
Long time since last update - we have just been inundated with some pretty remarkable cases (stay tuned).
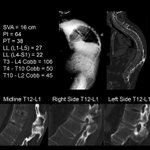
To conclude the last case, I initially tried to do a short segment from T10-L4 and focus on correcting the TL kyphosis with an ACR at the patient's only unfused segment at T12-L1 and an L2 PSO. CT looked great, but L4 fractured when he stood up, even after cement.
Revised by doing an L4 PSO to address the lumbar lordosis mismatch. Post-op 1.5 years out the patient is doing very well and 6 inches taller.
The real struggle of the case is whether we should've decided to do the long segment of the entire spine up front. Lots of previous comments focused on starting small - when do you all decide to go big up front?

Recently, I finished my 2nd year at OSU and saw a patient I took care of with @ViljoenMd about a year ago.
This is a 56 y/o patient with ank spondy and severe global kyphosis (on xray you can even see there's a ventral abdominal hernia from the kyphosis). I saw them for worsening back pain. The spine from C2-pelvis is fused except for T12-L1, which is en-route to developing a 3 column fracture.
How would you treat this? If you want to do a deformity correction surgery, where is the deformity and what would you do?
#neurosurgery #orthotwitter #spine #osumc

Recently, I finished my 2nd year at OSU and saw a patient I took care of with @ViljoenMd about a year ago.
This is a 56 y/o patient with ank spondy and severe global kyphosis (on xray you can even see there's a ventral abdominal hernia from the kyphosis). I saw them for worsening back pain. The spine from C2-pelvis is fused except for T12-L1, which is en-route to developing a 3 column fracture.
How would you treat this? If you want to do a deformity correction surgery, where is the deformity and what would you do?
#neurosurgery #orthotwitter #spine #osumc
Had an awesome time hosting our inaugural spine oncology course! Amazing group of attendees, faculty, and facilitates!

Hosted a talented group of senior residents at our inaugural OSU Spine Oncology Course. Thanks: Brad Elder MD, @Joshuapalmermd, @DavidSXu, and @bilskym
🔹Dynamic talks: Management of metastatic & primary tumors
🔹Cadaver dissections: En Bloc, Separation Surgery, MIS, Kyphoplasty

Our newest partner crushing it in his first week. 😬

David Xu, MD retweeted

First OR week as new faculty at OSU:
1. Thoracic fusion for Chance fx
2. 2-lvl ACDF
3. C1-2 fusion for pannus
4. C1-L1 epidural abscess
5. C1-2 fusion for fx
6. Thoracic arachnoid web
Great volume & case complexity here. Awesome residents, faculty & staff. Thanks for having me!
One of the best parts of being in academics is seeing the amazing growth of our med students. This is an all star group.
Here’s some of our awesome @OhioStateMed students with their posters at the Ohio State Neurosurgical Society meeting. Great work @adrianlam01, @Katelyn_Sette, Yamenah Ambreen, Jacob Ward, @JoshVignolles, Seth Wilson, and Annie Chen!

ALT Some of our great medical students with their posters

ALT Some of our great medical students with their posters
I recently went twitter blue because the complexity of cases and their discussion is increasing - case in point.
This is a 59 y/o who had an L2-5 fusion several years ago. She began deteriorating 2 years after surgery with worsening back pain. Beginning 1 year ago, she began having leg weakness. She presents wheelchair bound, unable to stand for more than 2-3 minutes or walk. Exam notable for 4-/5 in hip flexors and quads, clonus in ankles, and 3+ patellar and Achilles reflexes. Her original surgeon told her everything was "fine".
MRI shows severe stenosis at T10-T12 with cord signal change at T11. CT shows solid fusion from L2-4, L4-5 Pseudo. Xrays show sagittal deformity, stepwise spondylolisthesis in the T-spine, net lumbar kyphosis.
Measurements are in image, what would you do? What are your alignment goals and strategy?
#spine #neurosurgery #orthotwitter #osumc

Great feedback and thoughts on planning/goals of surgery. My view of the case was that there were 3 main pathologies:
1) Decompress the thoracic spine (as many pointed out, the most critical indication to proceed and address.)
2) Restore neutral alignment to TL-junction. Need to correct 28 degrees of L1-2 kyphosis. This needs an ACR versus 3-column osteotomy
3) Add additional L4-S1 lordosis. Even if L1-2 is neutralized, she still has a ~20 lordotic deficit.
My strategy was to do this in 2 stages instead of 1 stage with double 3COs. I started with an L1-2 lateral ACR with a 20 degree cage, preparing to do a laminectomy if there were any changes on monitoring. A week later, took the patient for T4-Pelvis, with an L1-2 PCO, TLIFs at L4-S1 and an L4-PSO. Went upper thoracic given the extensive decompression needed at T10-12 as well as the anticipated reciprocal thoracic kyphosis.
Patient did well! Cool to see restoration of normal thoracic kyphosis. Went to rehab 2 weeks later. Now able to walk/stand more than 10-15min. Still a long road ahead, but a very good start.

4
18
1,314
David Xu, MD retweeted

Congratulations to our Chairman @RussellLonser for being awarded the 2023 Distinguished Service Award from @CNS_Update #2023CNS. Well deserved! – at Washington, DC

ALT Dr. Lonser being presented the award

ALT Announcement of award
Complex situation. 59 y/o with T10-S1 construct, back pain, left L5 radic, arm weakness. Right & left delt and bicep 4/5, +hoffmans. Had 5 previous spine operations. Last surgery was L5-S1, now pseudo, TLIF spit out, S1 screw in canal.
What would you do and in what order? #spine

Thnx for all the discussion. Did cervical laminoplasty first. 3-month later, L5-S1 TLIF revision and an L4 PSO. Cage bit anterior, but hanging in there. Patient doing very well at 6 months.
Great recs on doing ALIF without back first in setting of pseudo. #neurosurgery #spine

3
8
678